The typical anion gap with albumin in the normal range is usually in the typical lab reference range used by the lab, often around 8 to 12 mEq/L when calculated without potassium, though the exact range depends on the laboratory’s approach and analyzer. The main point is that a normal albumin value offers a more reliable anion gap interpretation because albumin is one of the main unnamed anions that influences the result. If albumin is normal, the anion gap is less likely to be falsely low, and the result is more straightforward to use in acid-base balance review.
That said, the number should never be read in isolation. The best approach is to interpret the anion gap together with the electrolyte results, the blood electrolytes, and the full clinical picture. An Anion Gap Calculator can streamline the math, minimize mistakes, and enhance clinical accuracy when reviewing lab results.
What the Anion Gap Evaluates
The anion gap is a calculated value that helps clinicians identify hidden acid or undetected substances in the blood. It results from the gap between the main measured positive and negative ions in the serum electrolytes. The most common version uses sodium, chloride, and bicarbonate. Because not every charged particle in blood chemistry is directly measured, the anion gap estimates the balance of those unmeasured anions and related compounds.
In basic terms, the calculation reflects a basic principle of electrical neutrality. Blood must be kept electrically balanced, so if the measured ions do not fully account for that balance, the gap may point to the presence of acids or other substances not listed in the routine electrolyte panel. This makes it a valuable screening tool for a possible metabolic disorder.
Typical values come from the standard formula:
Anion gap = Sodium - (Chloride + Bicarbonate)
Because the result depends on the lab method, analyzer, and local reference interval, there is no single universal number. Still, understanding the expected range helps clinicians judge whether the result fits the patient’s clinical context.
Expected Anion Gap With Normal Albumin
With albumin within normal limits, the anticipated anion gap range is usually the same as the lab’s standard reference span. In many settings, that means about 8 to 12 mEq/L, though some laboratories use a slightly different reference interval. A typical albumin level means there is no need to adjust the result for protein-related effects, which makes easier interpretation.
Why does this matter? Because albumin is negatively charged and contributes substantially to the pool of hidden anions. When albumin is at a typical level, the expected anion gap is more stable and more indicative of true acid-base status. In other words, the measured gap is more likely to reflect the actual balance of acids, bases, and ions rather than being distorted by a low-protein state.
For everyday practice, a normal result does not necessarily indicate normal physiology, and a mildly elevated result does not always indicate disease. The number has to be https://anion-gap-range277.opalvector.com/posts/using-an-anion-gap-calculator-in-biochemical-testing interpreted with clinical context, any electrolyte disturbances, and whether the patient has symptoms or conditions that increase the likelihood of acidosis.
When albumin is normal, the reference interval for the anion gap is usually not adjusted unless the lab specifically uses a different method. This is why many clinicians use a calculator or formula-based approach to confirm the calculated result when the patient’s albumin status is uncertain.
How an Anion Gap Calculator Work
An Anion Gap Calculator serves as a simple clinical utility that performs the formula instantly once the user adds the electrolyte values. Many calculators use sodium, chloride, and bicarbonate from the electrolyte panel. Some versions also permit input of potassium, though the sodium-based version is the most commonly used in routine care.
The calculator assists reduce transcription errors and keeps the calculation faster when reviewing blood chemistry results. It is especially useful when clinicians need to move quickly from raw lab values to an interpretation of acid-base balance. In that way, the tool promotes accurate bedside reasoning and improves workflow during patient assessment.
Basic calculation steps include:
- Type in the serum sodium value. Input the serum chloride value. Input the bicarbonate value. Check the calculated anion gap. If albumin is low, use albumin correction to derive the corrected anion gap.
The calculator becomes especially valuable when a low or borderline result might otherwise be missed. Because the anion gap is a screening tool, the number should prompt further thinking rather than serve as a final diagnosis. It is best used alongside the blood gas, symptoms, and the rest of the metabolic picture.
Why Albumin Alters the Meaning
Albumin is a key negative-charge protein in blood and a leading contributor to the pool of unmeasured anions. When hypoalbuminemia is present, the anion gap may look lower than expected even if there is clinically important acid accumulation. This can lead to missed recognition of a metabolic problem if the clinician does not account for the protein effect.
That is why albumin correction matters. A low albumin value reduces the baseline anion gap, so a “normal” number may actually hide an elevated acid burden. The corrected anion gap adjusts for this and improves acid-base interpretation. In practice, this correction helps distinguish a truly normal gap from one that is falsely reassuring because of low protein.
This issue is central to accurate clinical context. For example, a patient with poor nutrition, inflammation, liver disease, or other causes of hypoalbuminemia can have a misleadingly low measured gap. By incorporating the serum albumin value, the clinician gets a more meaningful estimate of the true acid-base state.
Albumin correction is not a substitute for the full evaluation. It is one component of a broader approach that includes symptoms, medications, blood gas results, and the overall metabolic pattern. Still, it often improves diagnostic accuracy when evaluating possible acidosis.
Typical Reasons of a High or Normal Anion Gap
A elevated anion gap often points toward metabolic acidosis caused by too much acid being produced or reduced acid clearance. Frequent causes are lactic acidosis, ketoacidosis, and renal failure. These conditions elevates the amount of unmeasured acid in the blood, and increases the calculated gap.
Lactic acidosis may develop when oxygen delivery is impaired, tissue perfusion is poor, or lactate production increases because of illness or physiologic stress. Ketoacidosis develops when ketone bodies accumulate, often in settings such as insulin deficiency or prolonged fasting. Renal failure can raise acid levels in the blood because the kidneys cannot excrete them effectively.
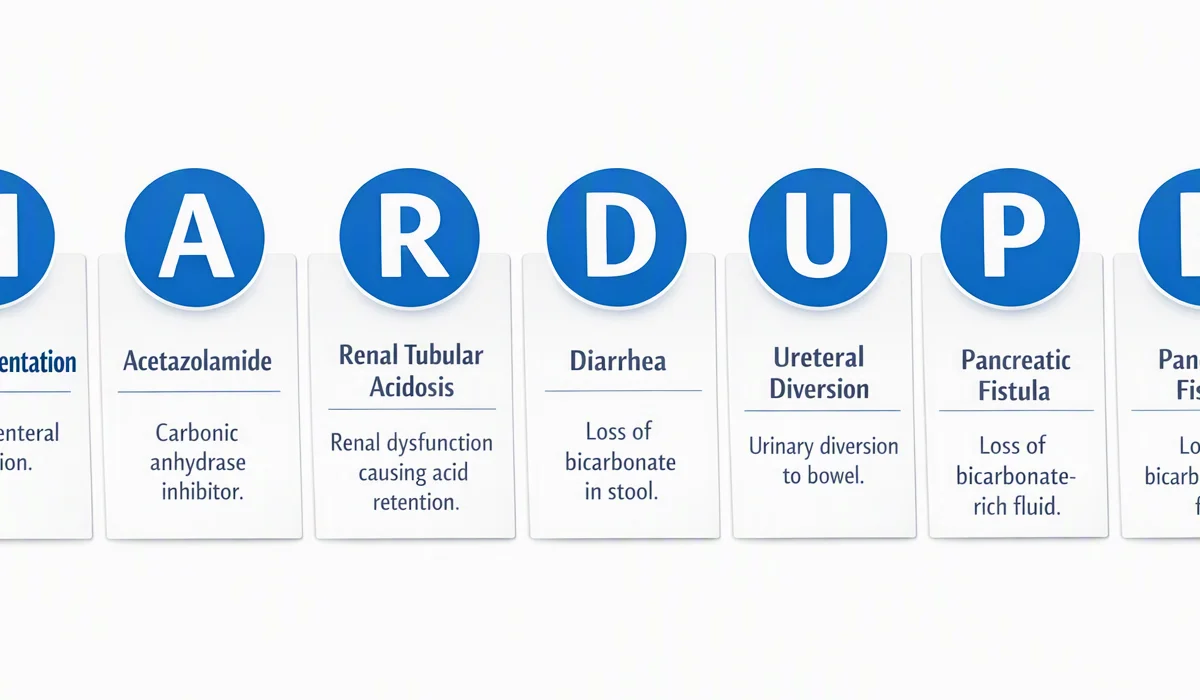
Sometimes the anion gap is normal even when acidosis is present. This does not rule out a metabolic problem. A normal gap pattern can occur in some types of non-gap metabolic acidosis, where bicarbonate is lost and chloride rises to maintain balance. That is why the anion gap should not be used alone to exclude disease.
Causes that influence interpretation include:
- Metabolic acidosis with increased acid load Lactic acidosis caused by poor oxygen delivery or tissue stress Ketoacidosis with ketone body accumulation Renal failure with decreased acid elimination
In each scenario, the best interpretation depends on the patient’s symptoms, medications, and other lab values. A calculator can help determine the pattern, but the diagnosis still depends on the full clinical picture.
When a Normal Anion Gap Can Be Inaccurate
A standard anion gap may be confusing when a mixed acid-base disorder is occurring. For example, one process may increase the gap while another lowers it, causing the measured result to appear seemingly normal. This is a well-known pitfall in complex hospitalized patients and in anyone with several concurrent illnesses.
Chronic kidney disease can also make difficult interpretation. Depending on the stage and associated metabolic changes, the patient may show alterations in bicarbonate, retained acids, and changing chloride levels. The resulting lab pattern may not fit a textbook case, so the anion gap must be considered alongside the rest of the data.
Laboratory variation is another reason a normal number may not reveal the whole story. Differences in measurement technique, analyzer calibration, and local reporting practices can alter the reference range. Even small changes in chloride or bicarbonate can change the final calculation, so minor differences should be evaluated carefully.
Unmeasured cations can also decrease the apparent gap. Substances such as certain ions or medications may offset the expected balance and make the anion gap seem smaller than anticipated. This does not automatically mean the result is wrong; it means the interpretation requires more clinical context.
Because of these limitations, the anion gap should be treated as part of a broader diagnostic strategy rather than a standalone answer. The value is most helpful when paired with the blood gas, symptoms, and albumin correction.
Understanding Values Step-by-Step
Interpreting the anion gap gets simpler when you follow a systematic approach. First with the observed electrolytes, then determine whether the result aligns with the patient’s overall presentation. This method improves consistency and minimizes the chance of missing a clinically significant acid-base problem.

Step 1: Review the serum albumin. If the serum albumin is normal, the standard anion gap is more dependable. If albumin is low, plan to calculate a corrected value so the result reflects the patient’s true acid-base state.
Step 2: Look at the electrolyte panel. Examine sodium, chloride, and bicarbonate carefully. The values in the electrolyte panel are the basis of the formula, and small shifts can change the result. Make sure the numbers correspond to the most recent blood chemistry sample.
Step 3: Compare the result with the blood gas. A blood gas can help determine whether the patient has acidemia or alkalemia and help clarify whether the anion gap is clinically important. If the calculated gap is elevated but the blood gas does not support acidosis, think about a mixed process or an alternate cause.
Step 4: Apply clinical context. Take into account the patient’s symptoms, history, medications, and risk factors. A high gap in a patient with diabetes, poor perfusion, or kidney dysfunction may point toward different causes than the same value in a stable patient. Good patient assessment always ties the math to the bedside picture.
Step 5: Use the corrected result if needed. If albumin is abnormal, the corrected anion gap may identify a hidden abnormality. This correction is especially useful when evaluating possible acidosis because it improves the interpretation of a borderline or falsely normal value.
Following these steps helps make the result clinically meaningful rather than merely numerical. The goal is to understand whether the patient has an acid-base disturbance, what type it is, and how urgent it may be.
FAQ on Expected Anion Gap With Normal Albumin
What’s the expected anion gap when albumin is normal?
If albumin is normal, the expected anion gap usually stays within the lab’s standard reference range, often around 8 to 12 mEq/L without potassium. The exact anion gap range is influenced by the analyzer and local reporting method, so the laboratory’s own interval should be used for final interpretation.
Does normal albumin change the anion gap reference range?
Usually not. If normal albumin is present, the standard reference range generally applies without albumin correction. Normal protein levels make the measured gap more straightforward to interpret because the contribution from unmeasured anions is less distorted.
How do you calculate a corrected anion gap for low albumin?
A corrected anion gap modifies the measured value upward when hypoalbuminemia is present. The exact correction method can vary, but the general idea is to account for the missing negative charge from low serum albumin. An Anion Gap Calculator can simplify this formula and improve the corrected result.
Can a normal anion gap still mean there is acidosis?
Certainly. A normal gap does not exclude metabolic acidosis. Some patients have a normal-gap metabolic acidosis, while others have a mixed acid-base disorder that masks an elevated gap. That is why the result should always be interpreted with the blood gas, the electrolyte pattern, and the overall clinical context.
When should an Anion Gap Calculator be used?
An Anion Gap Calculator is useful any time you want a quick, accurate calculation from the electrolyte panel, especially if there is concern for acidosis, electrolyte abnormalities, or abnormal serum albumin. It is especially helpful for bedside review, when applying albumin correction, and when improving diagnostic accuracy in routine lab results.