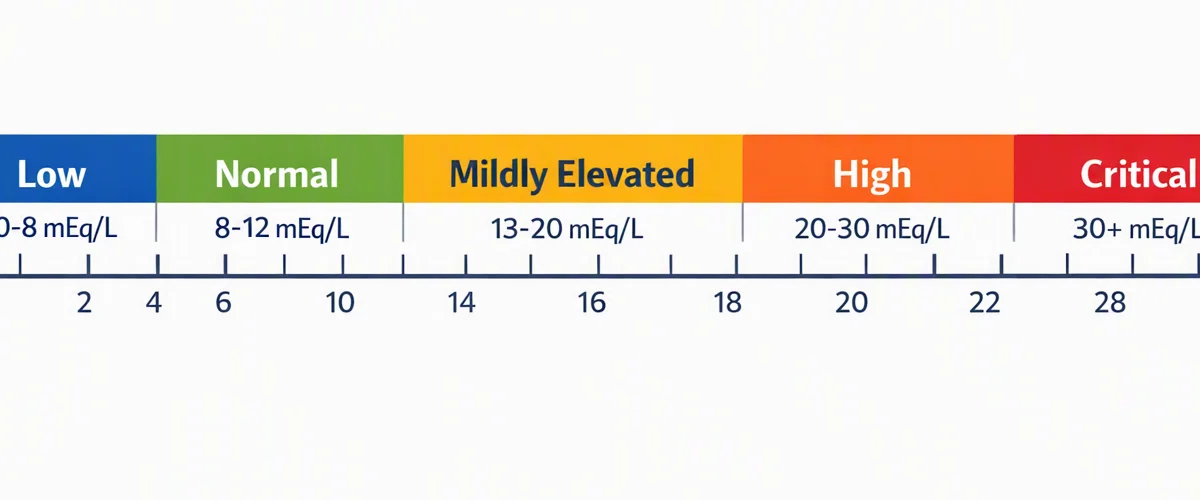
The expected anion gap with normal albumin is usually within the standard reference range used by the laboratory, often around 8 to 12 mEq/L when calculated without potassium, though the specific range depends on the lab’s method and analyzer. The key point is that a normal albumin value helps provide a more reliable anion gap result because albumin is one of the main unmeasured anions that influences the result. If albumin is normal, the anion gap is less likely to be falsely low, and the result is simpler to use in acid base balance review.
That said, the number should never be read in isolation. The most practical approach is to interpret the anion gap together with the electrolyte panel, the blood electrolytes, and the full clinical picture. An Anion Gap Calculator can streamline the computation, limit mistakes, and increase diagnosis accuracy when reviewing lab results.
How the Anion Gap Evaluates
The anion gap is a derived value that enables clinicians detect hidden acid or unlisted substances in the blood. It results from the gap between the main measured positive and negative ions in the serum electrolytes. The most common version uses sodium, chloride, and bicarbonate. Because not every charged particle in blood chemistry is directly measured, the anion gap estimates the balance of those unmeasured anions and related compounds.
In simple terms, the calculation shows a basic principle of electrical neutrality. Blood must be kept electrically balanced, so if the measured ions do not fully account for that balance, the gap may suggest the presence of acids or other substances not listed in the routine electrolyte panel. This makes it a useful screening tool for a possible metabolic disorder.
Typical values are based on the standard formula:
Anion gap = Sodium - (Chloride + Bicarbonate)
Because the result depends on the lab method, analyzer, and local reference interval, there is no single universal number. Still, understanding the expected range helps clinicians judge whether the result fits the patient’s clinical context.
Predicted Anion Gap With Normal Albumin
With a normal albumin level, the typical anion gap span is usually the similar to the lab’s standard reference span. In many cases, that means about 8 to 12 mEq/L, though some laboratories use a slightly different reference range. A healthy albumin level means there is no need to correct the result for protein-related effects, which streamlines interpretation.
Why is this important? Because albumin is negatively charged and contributes substantially to the pool of hidden anions. When albumin is normal, the expected anion gap is more stable and more indicative of true acid-base status. In other words, the measured gap is more likely to reflect the actual balance of acids, bases, and ions rather than being distorted by a low-protein state.
For clinical use, a normal result does not necessarily indicate normal physiology, and a mildly elevated result does not always suggest disease. The number has to be interpreted with clinical context, any electrolyte abnormalities, and whether the patient has symptoms or conditions that increase the likelihood of acidosis.
When albumin is normal, the reference interval for the anion gap is usually not adjusted unless the lab specifically uses a different method. This is why many clinicians use a calculator or formula-based approach to confirm the calculated result when the patient’s albumin status is uncertain.
How does an Anion Gap Calculator Work
An Anion Gap Calculator serves as a simple clinical device that applies the formula automatically and quickly once the user enters the electrolyte values. Most calculators use sodium, chloride, and bicarbonate from the electrolyte panel. Some versions also support input of potassium, though the sodium-based version is the most frequently used in routine care.
The calculator helps reduce transcription errors and renders the calculation more rapid when reviewing blood chemistry results. It is especially useful when clinicians need to move quickly from raw lab values to an interpretation of acid-base balance. In that way, the tool enhances accurate bedside reasoning and improves workflow during patient assessment.
Basic calculation steps consist of:
- Type in the serum sodium value. Input the serum chloride value. Enter the bicarbonate value. Check the calculated anion gap. If albumin is low, add albumin correction to derive the corrected anion gap.
The calculator becomes particularly valuable when a low or borderline result might otherwise be missed. Because the anion gap is a screening tool, the number should encourage further thinking rather than function as a final diagnosis. It is best used alongside the blood gas, symptoms, and the rest of the metabolic picture.
How Albumin Affects the Assessment
Albumin is a important negatively charged protein in blood and a significant contributor to the pool of unmeasured anions. When hypoalbuminemia is present, the anion gap may appear lower than expected even if there is clinically important acid accumulation. This can lead to under-recognition of a metabolic problem if the clinician does not account for the protein effect.
That is why albumin correction matters. A low albumin value reduces the baseline anion gap, so a “normal” number may actually conceal an elevated acid burden. The corrected anion gap adjusts for this and improves acid-base interpretation. In practice, this correction helps distinguish a truly normal gap from one that is falsely reassuring because of low protein.
This issue is central to accurate clinical context. For example, a patient with poor nutrition, inflammation, liver disease, or other causes of hypoalbuminemia can have a misleadingly low measured gap. By incorporating the serum albumin value, the clinician gets a more meaningful estimate of the true acid-base state.
Albumin correction is not a substitute for the full evaluation. It is one component of a broader approach that includes symptoms, medications, blood gas results, and the overall metabolic pattern. Still, it often improves diagnostic accuracy when evaluating possible acidosis.
Common Causes of a High or Normal Anion Gap
A elevated anion gap often suggests metabolic acidosis caused by increased acid generation or reduced acid clearance. Typical causes include lactic acidosis, ketoacidosis, and renal failure. Each of these conditions increases the amount of unmeasured acid in the blood, and increases the calculated gap.
Lactic acidosis can happen when oxygen delivery is impaired, tissue perfusion is poor, or lactate production goes up because of illness or physiologic stress. Ketoacidosis develops when ketone bodies accumulate, often in settings such as insulin deficiency or prolonged fasting. Renal failure can lead to more acids in the blood because the kidneys cannot eliminate them efficiently.
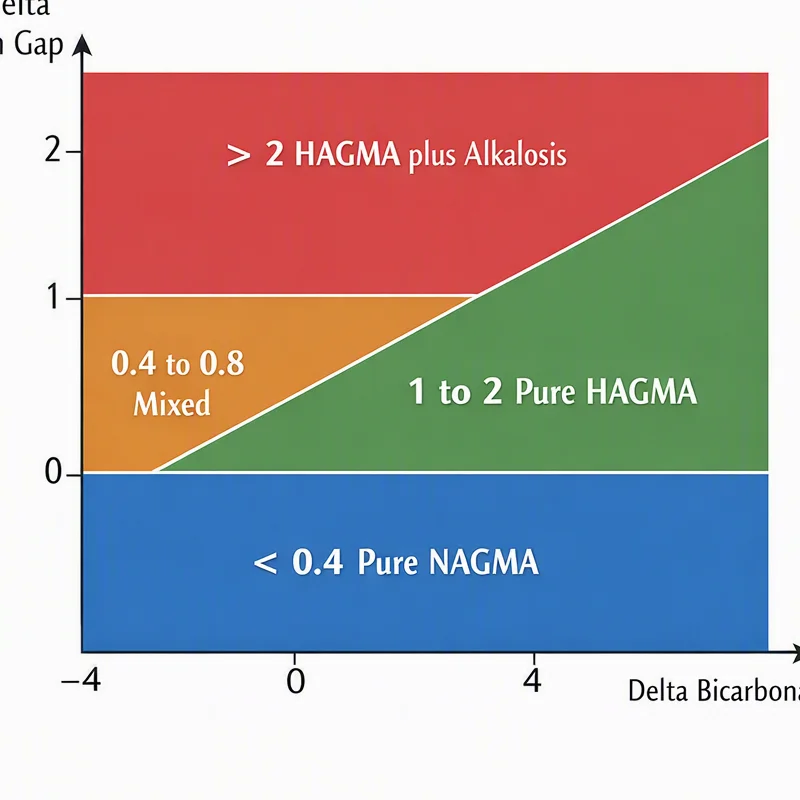
Sometimes the anion gap is not elevated even when acidosis is present. This does not rule out a metabolic problem. A normal gap pattern can occur in some types of non-gap metabolic acidosis, where bicarbonate is lost and chloride rises to maintain balance. That is why the anion gap should not be used alone to exclude disease.
Factors affecting interpretation include:
- Metabolic acidosis with a higher acid burden Lactic acidosis from impaired oxygen delivery or tissue stress Ketoacidosis due to ketone buildup Renal failure with impaired acid removal
In each scenario, the most accurate interpretation depends on the patient’s symptoms, medications, and other lab values. A calculator can assist in finding the pattern, but the diagnosis still depends on the full clinical picture.
When a Typical Anion Gap Can Be Misleading
A normal anion gap may be deceptive when a overlapping acid-base disorder is present. For example, one process may raise the gap while https://anion-gap-range805.almoheet-travel.com/anion-gap-calculator-for-plasma-electrolytes another reduces it, causing the measured result to appear seemingly normal. This is a common pitfall in complex hospitalized patients and in anyone with more than one concurrent illnesses.
Chronic kidney disease can also complicate interpretation. Depending on the stage and associated metabolic changes, the patient may show changes in bicarbonate, retained acids, and changing chloride levels. The resulting lab pattern may not fit a textbook case, so the anion gap must be reviewed alongside the rest of the data.
Laboratory variation is another reason a normal number may not tell the whole story. Differences in measurement technique, analyzer calibration, and local reporting practices can alter the reference range. Even small changes in chloride or bicarbonate can affect the final calculation, so minor differences should be read carefully.
Unmeasured cations can also reduce the apparent gap. Substances such as certain ions or medications may disrupt the expected balance and make the anion gap seem smaller than anticipated. This does not automatically mean the result is wrong; it means the interpretation requires more clinical context.
Because of these issues, the anion gap should be treated as part of a more comprehensive diagnostic strategy rather than a standalone answer. The value is most helpful when paired with the blood gas, symptoms, and albumin correction.
Interpreting Results Step-by-Step
Interpreting the anion gap is easier when you use a structured process. Begin with the measured electrolytes, then decide whether the result aligns with the patient’s overall presentation. This approach enhances consistency and reduces the chance of missing a clinically significant acid-base problem.
Step 1: Review the serum albumin. If the serum albumin is unremarkable, the standard anion gap is more reliable. If albumin is low, plan to calculate a corrected value so the result reflects the patient’s true acid-base state.
Step 2: Look at the electrolyte panel. Review sodium, chloride, and bicarbonate carefully. The values in the electrolyte panel are the core of the formula, and small shifts can change the result. Make sure the numbers match the most recent blood chemistry sample.
Step 3: Compare the result with the blood gas. A blood gas can show whether the patient has acidemia or alkalemia and make clear whether the anion gap is clinically important. If the calculated gap is elevated but the blood gas does not support acidosis, look for a mixed process or an alternate cause.
Step 4: Apply clinical context. Take into account the patient’s symptoms, history, medications, and risk factors. A high gap in a patient with diabetes, poor perfusion, or kidney dysfunction may indicate different causes than the same value in a stable patient. Good patient assessment always connects the math to the bedside picture.
Step 5: Use the corrected result if needed. If albumin is abnormal, the corrected anion gap may uncover a hidden abnormality. This correction is especially useful when evaluating possible acidosis because it strengthens the interpretation of a borderline or falsely normal value.
Using these steps helps make the result clinically meaningful rather than merely numerical. The goal is to understand whether the patient has an acid-base imbalance, what type it is, and how urgent it may be.
FAQ: Expected Anion Gap With Normal Albumin
What’s the expected anion gap when albumin is normal?
When albumin is normal, the expected anion gap usually stays within the lab’s standard reference range, often around 8 to 12 mEq/L without potassium. The exact anion gap range varies by the analyzer and local reporting method, so the laboratory’s own interval should be used for final interpretation.
Does normal albumin change the anion gap reference range?
Usually not. If normal albumin is present, the standard reference range generally applies without albumin correction. Normal protein levels make the measured gap more straightforward to read because the contribution from unmeasured anions is less affected.
How do you calculate a corrected anion gap for low albumin?
A corrected anion gap raises the measured value upward when hypoalbuminemia is present. The exact correction method can vary, but the general idea is to account for the missing negative charge from low serum albumin. An Anion Gap Calculator can make easier this formula and improve the corrected result.
Can a normal anion gap still mean there is acidosis?
Yes. A normal gap does not exclude metabolic acidosis. Some patients have a normal-gap metabolic acidosis, while others have a mixed acid-base disorder that masks an elevated gap. That is why the result should always be interpreted with the blood gas, the electrolyte pattern, and the overall clinical context.

When should an Anion Gap Calculator be used?
An Anion Gap Calculator is useful whenever you want a quick, accurate calculation from the electrolyte panel, especially if there is concern for acidosis, electrolyte abnormalities, or abnormal serum albumin. It is especially helpful for bedside review, when applying albumin correction, and when improving diagnostic accuracy in routine lab results.