How the anion gap evaluates
The anion gap is a useful way to look at the balance of electrolytes in the blood and to check acid-base balance. It is not a direct measurement of a single substance. Instead, it is a computed value that shows the difference between positive and negatively charged particles in the bloodstream. Clinicians often use it as a clue when investigating metabolic acidosis and other acid-base disorder patterns.
In clinical terms, the anion gap helps determine whether there may be unmeasured acids or other abnormal substances affecting serum levels. Because it is derived from common lab values, it is a valuable diagnostic tool when reviewing blood test results. The result can point toward an electrolyte imbalance or another metabolic disorder that needs more workup.
Although the number itself is easy to interpret, its clinical significance depends on the whole picture. A mildly abnormal result may be less concerning than a dramatic change with symptoms. That is why an anion gap should always be considered alongside the patient’s condition, the reference range, and the rest of the chemistry results.
In what way an anion gap calculator functions
An Anion Gap Calculator takes basic lab values to calculate anion gap rapidly and reliably. Most calculators ask for sodium, chloride, and bicarbonate, which are usually shown on a standard chemistry report. By entering those values, the calculator performs the anion gap formula and returns a result that can be compared with the expected reference range.
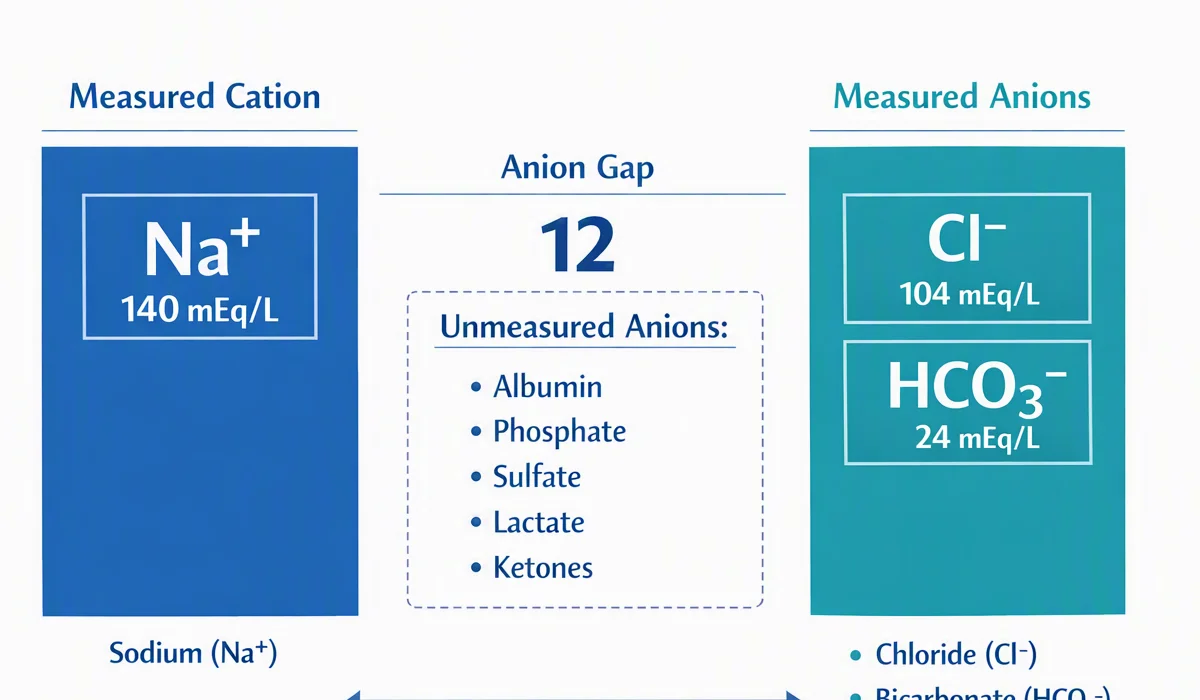
The reason this functions is that sodium is the main measured cation, while chloride and bicarbonate account for major measured anions. The difference between them offers a useful estimate of unmeasured ions in the blood. When the gap is widened, clinicians may look for acids that are not directly measured on a routine electrolyte panel.
An Anion Gap Calculator is especially useful when reviewing complex blood test results or checking whether an abnormal value fits the overall pattern. It can support quicker interpretation, but it does not replace clinical judgment. The same number can have varying meaning depending on the patient, the lab method, and the other lab values present.
Anion gap formula and example calculations
The most widely used anion gap expression is:
Anion gap = serum sodium − (serum chloride + serum bicarbonate)
This formula uses serum sodium, serum chloride, and serum bicarbonate from a standard chemistry panel. Some labs use a slightly different method, and some include potassium in older versions of the equation, but the sodium-based version is widely used in clinical practice.
Example 1: if the serum sodium is 140, the serum chloride is 102, and the serum bicarbonate is 24, the anion gap is 140 − (102 + 24) = 14. This value may sit inside the lab reference range depending on the method used.
Example 2: when the serum sodium is 138, the serum chloride is 100, and the serum bicarbonate is 12, the anion gap is 138 − (100 + 12) = 26. A higher value suggests high anion gap metabolic acidosis and should lead to review of the full clinical picture.
Example 3: when the sodium is normal but bicarbonate is low with a normal gap, this may point toward normal anion gap metabolic acidosis. The calculator can help identify the pattern, but interpretation depends on the cause and associated findings.
Normal anion gap interval and what affects it
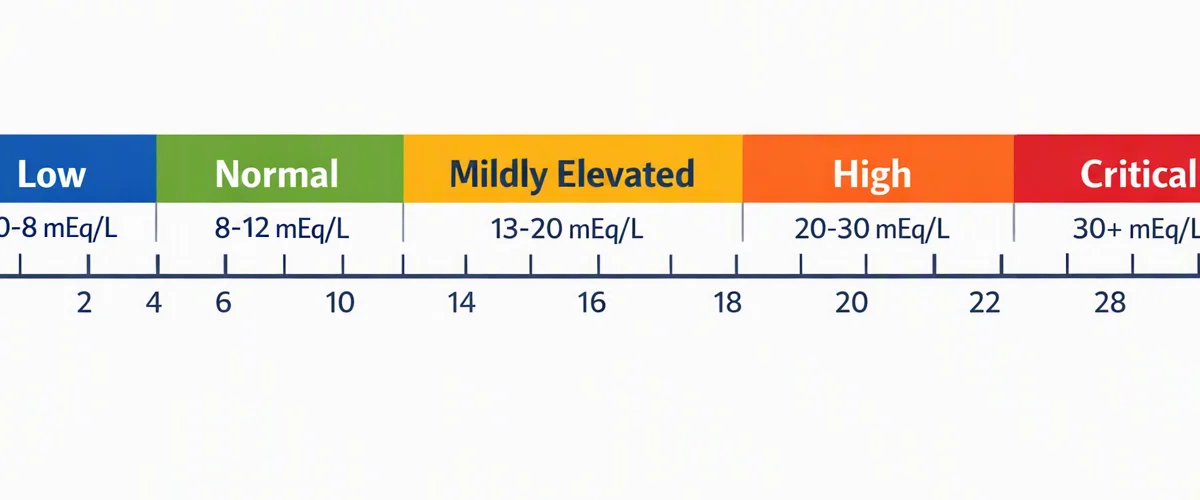
The expected range for anion gap differs by laboratory because of differences in testing methods and reporting practices. This is why the lab reference range listed on the report is more important than a single cutoff. A result that looks high in one lab may be expected in another.
Albumin is one of the most important factors that impacts the result. Since albumin is a anionic protein, lower albumin levels can make the gap appear reduced than it truly is. In patients with low albumin, albumin correction may be needed to help estimate the true gap. This is a reason a single number should not be interpreted in isolation by itself.
Other influences include alterations in measured cations, shifts in protein levels, and variations in analyzer techniques. Some medications, toxins, and uncommon blood proteins can also affect the value. For this reason, interpreting the anion gap is not just a math problem; it is a review of chemistry, context, and pattern recognition.
High anion gap vs normal anion gap
A elevated result often suggests high anion gap metabolic acidosis, which occurs when excess acids build up in the blood. Common causes include lactic acidosis, ketoacidosis, and kidney failure. In these settings, bicarbonate is consumed as the body neutralizes excess acid, and the gap rises because the missing bicarbonate is replaced by unmeasured anions.
Lactic acidosis can occur when tissues do not get enough oxygen, when severe infection is present, or when other systemic stressors drive lactate production. Ketoacidosis is often associated with diabetes, alcohol use, or prolonged fasting. Kidney failure can reduce the body’s ability to clear acids, which also increases the gap.
By contrast, normal anion gap metabolic acidosis usually reflects a loss of bicarbonate rather than buildup of unmeasured acid. Common mechanisms include gastrointestinal bicarbonate loss or renal tubular problems. The gap stays normal because chloride often rises to compensate for the loss of bicarbonate, even though the patient still has an acid-base problem.
Understanding whether the pattern is high or normal is a major step in the interpretation of the result. Both patterns can indicate a serious metabolic disorder, but they point toward different underlying cause pathways and therefore different next steps.
Low anion gap causes along with clinical meaning
A reduced anion gap is rarer than a high one, but it can still be clinically meaningful. One of the most common reasons is hypoalbuminemia, because albumin contributes significantly to the https://anion-gap-analyzer309.tearosediner.net/what-results-in-high-anion-gap-metabolic-acidosis unmeasured anions in blood. When albumin is low, the gap may decrease even if there is no true acid-base abnormality.
Albumin correction is especially important here. If the albumin is low, a corrected calculation may reveal that the apparent low gap is mostly explained by reduced protein levels rather than a separate disorder. This avoids overcalling an abnormal result and assists focus on the real issue.
Other factors include lab artifact, elevated unmeasured positively charged proteins, and certain medications or toxins. Multiple myeloma is a classic clinical association because abnormal immunoglobulins can decrease the gap. Lithium exposure can also lower the gap because lithium is an unmeasured cation that may shift the balance of charged particles.
A low value should not be dismissed, but it should also not be overinterpreted without the full picture. The result may reflect protein changes, medication effects, or measurement issues rather than a dangerous acid-base problem. That is why review of the full chemistry report and clinical scenario is crucial.
How to interpret anion gap in blood test results
Good interpretation of blood tests begins with the whole electrolyte panel, not only one number. The anion gap should be considered alongside sodium, chloride, bicarbonate, kidney function, glucose, and other important abnormal labs. A single abnormal result may be less important than a repeated pattern across several measurements.
To begin, confirm that the values came from a trusted blood chemistry test and that the reported normal range used by the lab matches the method used by that lab. Then, look at the bicarbonate level. If bicarbonate is low, ask whether the anion gap is high, normal, or low, because that distinction can help narrow the diagnosis.
After that, consider the overall clinical picture. Symptoms, recent illness, medications, fluid status, kidney function, and nutrition all play a role. For example, low albumin from chronic illness can change the interpretation, while signs of infection or poor perfusion may make lactic acidosis more likely. This is where the calculator becomes not merely a mathematical shortcut; it supports structured clinical reasoning.
It is also important to remember that the anion gap is a screening clue, not a final diagnosis. A result can point to an acid-base pattern, but it does not by itself identify the exact cause. The right next step may include repeat testing, albumin correction, blood gas analysis, or additional studies based on the scenario.
When to seek clinical evaluation
Any atypical anion gap should be considered together with symptoms and the broader context. Small shifts without symptoms may simply need reassessment and repeat testing. However, a substantial change from the expected range, especially with low bicarbonate, may indicate severe acidosis that needs immediate evaluation.
Signs such as rapid breathing, confusion, severe weakness, vomiting, chest pain, dehydration, or worsening illness can suggest a more significant problem. In these cases, emergency care may be advised, especially if the blood chemistry shows a marked disturbance or the person is visibly unwell.
Physician review is important whenever the result is surprising, persistent, or paired with other concerning findings. This is particularly true if there is existing kidney disease, diabetes, toxic exposure, infection, or unexplained changes in mental status. A clinician can link the lab pattern with symptom assessment and decide whether additional treatment or testing is needed.
Common questions about anion gap blood tests
What is an anion gap calculator used for?
An anion gap calculator is used to rapidly estimate the anion gap from routine blood chemistry values. It helps clinicians and patients interpret blood test results, identify possible acid-base disturbances, and decide whether the pattern fits a high, normal, or low gap. It is a practical diagnostic tool, but it works best when used with the full clinical picture.
How do you calculate anion gap from blood test results?
To calculate anion gap, use the common anion gap formula: serum sodium minus the sum of serum chloride and serum bicarbonate. In other words, serum sodium − ( serum chloride + serum bicarbonate). This can be done manually or with an Anion Gap Calculator using values from a blood chemistry panel.
What does a high anion gap mean?
A raised result often may indicate high anion gap metabolic acidosis, meaning there may be additional unmeasured acids in the blood. Frequent causes include lactic acidosis, ketoacidosis, and kidney failure. The result should be interpreted with other lab values and the patient’s clinical context.
What can cause a low anion gap?
A low anion gap is often associated with hypoalbuminemia, since low albumin decreases the number of unmeasured anions. Other causes include multiple myeloma, lithium exposure, and occasional lab-related issues. If albumin is low, albumin correction may change the interpretation.
Should albumin be included when interpreting the anion gap?
Yes, albumin should be included because it significantly affects the result. If albumin is low, the raw number may not reflect the true gap, which is why albumin correction is often important. Including albumin increases the accuracy of blood test interpretation and helps minimize missed acid-base abnormalities.