An Anion Gap Calculator is a useful instrument for determining the anion gap from routine blood chemistry results. By using sodium, chloride, and bicarbonate values, it assists clinicians and students quickly assess acid-base balance and notice patterns that may point to an underlying disorder. Because these numbers are already part of a typical serum chemistry panel, the calculation can be performed promptly as a diagnostic aid during everyday review of an electrolyte panel.
This guide focuses on calculator use with chloride values and bicarbonate values, how the anion gap calculation works, and how to understand the result in day-to-day clinical context. It also reviews formula variations, including potassium and albumin adjustments, so you can better understand the corrected anion gap when needed.
Understanding the Anion Gap?
The anion gap is a computed number that indicates the discrepancy between measured cations and measured anions in the blood. It is a method to evaluate whether there may be additional unmeasured anions influencing the body’s acid-base balance. In standard practice, the calculation is obtained from serum electrolytes listed on a serum chemistry panel or broader blood chemistry test.
Although the anion gap is not a straightforward measurement of a single substance, it is helpful because shifts in the number can point toward an acid-base disorder or another form of metabolic derangement. A typical result does not eliminate disease, but an abnormal result can direct further evaluation and help clarify the underlying cause.
In clinical terms, the anion gap is often used as a screening tool when interpreting electrolyte patterns. It is especially helpful when a patient has signs of metabolic acidosis, since the result can suggest whether the condition involves elevated acids, loss of bicarbonate, or another imbalance in the body’s buffer system.
In what way an Anion Gap Calculator Operates
An Anion Gap Calculator applies a straightforward formula based on standard laboratory measurements. The calculator often asks for sodium, chloride, and bicarbonate values, then performs the anion gap formula on its own. This helps simplify the process to get a fast result without doing the math by hand.
The classic version of the calculation is:
Anion gap = sodium - chloride - bicarbonate
Some calculators display the result using the same structure as Na minus Cl minus HCO3. In that format, sodium is the main measured cation, while chloride and bicarbonate are the principal measured anions. The difference between them approximates the amount of unmeasured anions in the blood.
For a user, the workflow is clear:
- Input the sodium value from the lab report. Type in the chloride value. Type in the bicarbonate value, often listed as CO2 or HCO3. Review the calculated anion gap and contrast it with the lab’s reference range.
This approach is especially useful when reviewing routine serum electrolytes and trying to determine whether an electrolyte imbalance may be altering the overall pattern.
Anion Gap Formula and Typical Variations
The most familiar formula is Na minus Cl minus HCO3, but there are regular variations depending on the testing facility and clinical setting. Some clinicians add potassium in the formula, which slightly modifies the result slightly. Others rely on the sodium-based calculation because potassium plays a smaller role to the routine interpretation in many settings.
One reason for variation is that the anion gap is influenced by factors such https://anion-gap-guide100.trexgame.net/anion-gap-calculator-for-assessing-changes-in-anion-gap as albumin, a major unmeasured negatively charged protein. When albumin is low, the measured gap may appear decreased than expected. In those cases, a corrected anion gap may give a more accurate estimate of the patient’s true status.
Albumin correction matters because albumin is one of the largest contributors to the normal gap. If albumin drops, the calculated number can underestimate the burden of unmeasured anions. A corrected value can therefore enhance the clinical picture, especially when evaluating a possible acid-base disorder.
Useful points to keep in mind:
- The calculator may use sodium, chloride, and bicarbonate only. Some formulas incorporate potassium, which can slightly increase the gap. Albumin adjustment may be needed when protein levels are off. Always check the result with the relevant laboratory reference interval.
Because formulas differ, the same patient may have somewhat different results depending on the method used. That is why understanding the specific anion gap formula built into the calculator is important for accurate interpretation.
Understanding the Outcome
Understanding the result usually starts from the lab’s reference range. Results are often categorized as normal anion gap, high anion gap, or low anion gap. The exact value range varies by laboratory and by whether potassium is taken into account, so the calculator should always be reviewed with the reported local range.
A typical anion gap suggests that the equilibrium of measured ions is within expected limits. That said, a normal finding does not exclude disease, particularly if other results point to a meaningful acid-base imbalance. For example, a patient may still have metabolic imbalances that are better interpreted through the bicarbonate level, chloride level, and overall clinical picture.
A raised anion gap typically indicates higher acid levels or presence of unmeasured compounds. In contrast, a decreased anion gap is uncommon and may suggest reduced albumin, testing issues, or certain disorders that alter the electrolyte pattern.
When considering interpretation, it helps to ask:
- Is the result within the stated reference range? Are the chloride and bicarbonate values compatible with the gap? Does the patient have signs of metabolic acidosis or another metabolic derangement? Could albumin be altering the apparent result?
Because the anion gap is a diagnostic aid, not a final diagnosis, interpretation should always be considered alongside the rest of the lab data and the patient’s symptoms.
Causes of a Elevated Anion Gap
A elevated anion gap often suggests accumulation of acids or other undetected substances in the blood. Amongst the primary causes are lactic acidosis, ketoacidosis, renal failure, and contact to toxic alcohols. These conditions can all produce a marked acid load or reduce the body’s ability to clear acids efficiently.
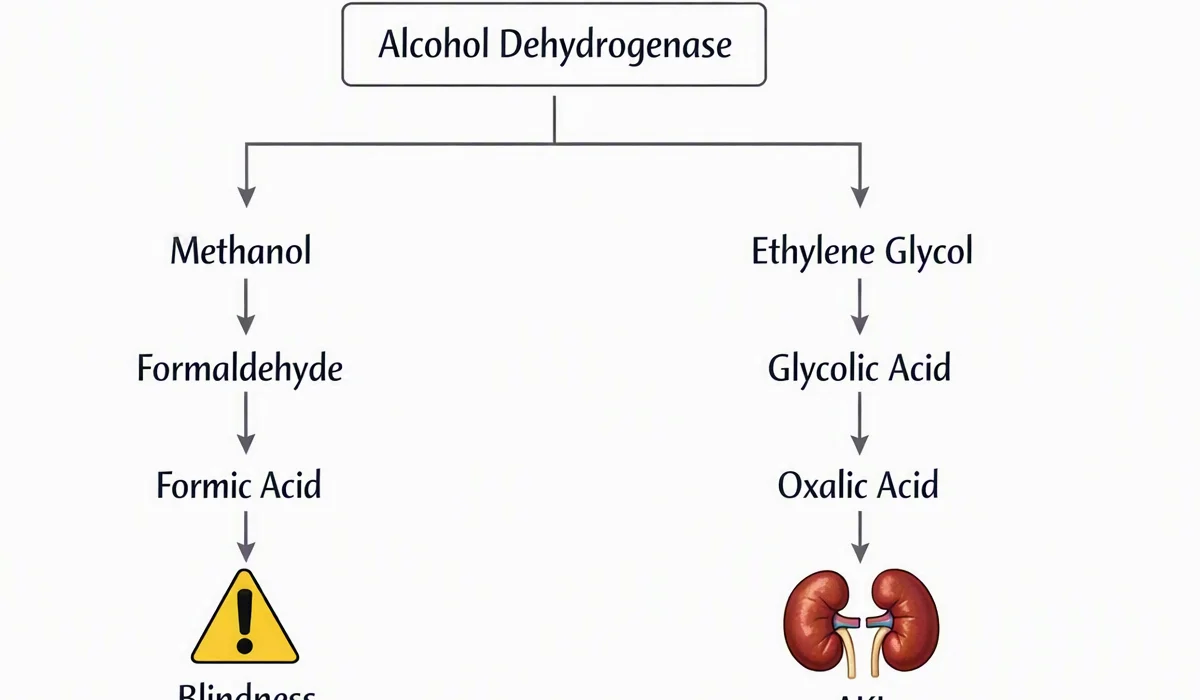
Lactic acidosis occurs when lactate rises, often in settings of reduced tissue oxygen delivery, severe illness, or other physiologic stress. Ketoacidosis may occur when ketone production goes up, such as in uncontrolled diabetes, prolonged fasting, or alcohol-related metabolic changes. Renal failure can hinder acid excretion, allowing acids to accumulate. Toxic alcohols are a classic cause of a high gap and should be considered when the history or presentation suggests ingestion.
These causes are often evaluated together with the patient’s bicarbonate level, since a low bicarbonate value frequently accompanies high-gap metabolic acidosis. However, the exact pattern can vary, which is why the Anion Gap Calculator is best used as part of a broader workup rather than in isolation.
Origins of Low Anion Gap
A reduced anion gap is uncommon yet still clinically important. A key cause is hypoalbuminemia, because albumin is a major unmeasured anion. If albumin drops, the calculated gap may decrease even if no other major disorder is present.
Another frequent cause is lab error. Since the anion gap depends on sodium, chloride, and bicarbonate, even small measurement problems can affect the result. A repeat test may be appropriate if the finding does not fit the clinical picture.
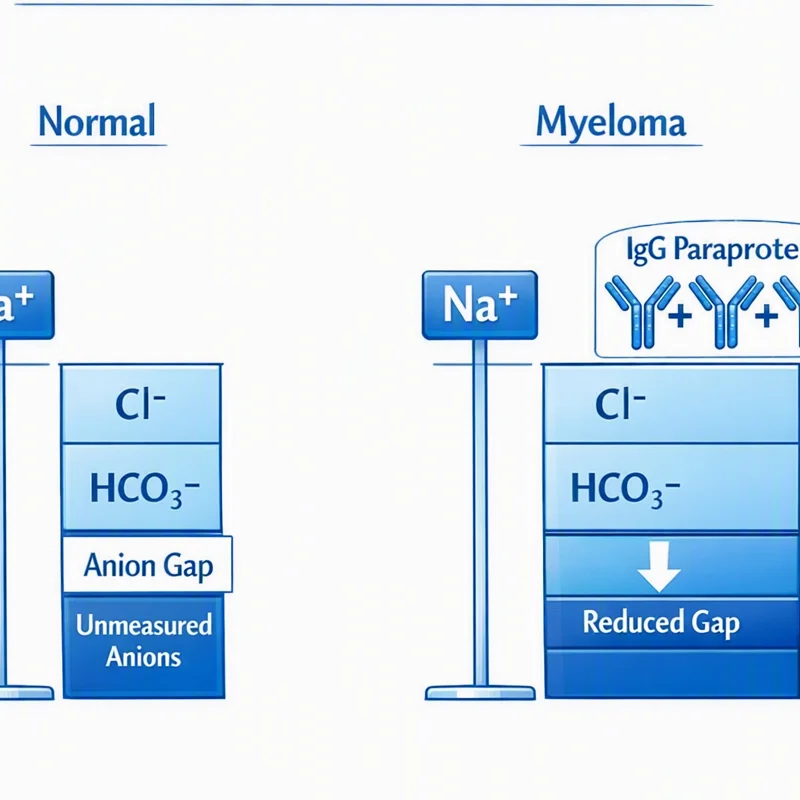
Other reasons may include hypercalcemia and multiple myeloma. In some cases, abnormal proteins or changes in other measured ions alter the balance enough to lower the gap. When the result is unexpectedly low, checking albumin and considering a corrected anion gap can be particularly helpful.
In summary, a low result should not be dismissed. It can indicate an actual underlying condition, or it may be a clue that the calculator output needs to be rechecked against the actual laboratory values and the broader clinical context.
How Chloride and Bicarbonate Are Important
The chloride level and bicarbonate level are key to the calculation because they are the primary measured anion inputs used in most versions of the formula. When chloride rises or bicarbonate falls, the gap can change rapidly, which makes these numbers especially helpful in evaluating electrolyte disturbance and acidic metabolic state.
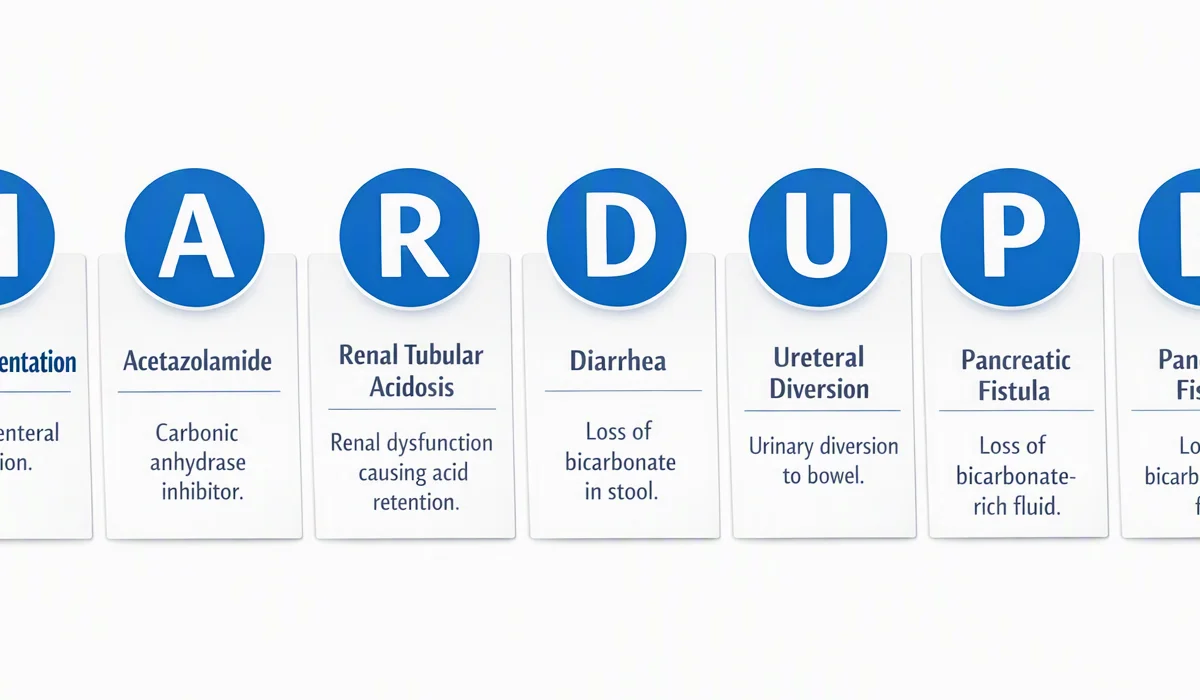
Chloride often increases in conditions where bicarbonate is lost or diluted, while bicarbonate commonly decreases in acidotic states. The relationship between the two provides insight into how the body is handling acids and bases. This is why anion gap review is often part of the broader assessment of acid base balance.
Using chloride and bicarbonate values together can reveal patterns that might not be obvious from either number alone. For example, a low bicarbonate with a normal or elevated chloride may point to a different process than a low bicarbonate with a high gap. This makes the anion gap a practical way to structure the interpretation of serum electrolytes.
Step by Step Example Calculation
Here is a basic example using typical example values to show the manual calculation process.
- Sodium = 140 Chloride = 104 Bicarbonate = 24
Using the anion gap formula:
Anion gap = sodium - chloride - bicarbonate
Insert the values:
140 - 104 - 24 = 12
The anion gap result in this example is 12. If the laboratory’s normal range includes 12, then this would be interpreted as a normal anion gap. If the lab’s range differs, the interpretation should follow the local laboratory reference.
Now consider a second example:
- Sodium = 138 Chloride = 100 Bicarbonate = 16
Calculation:
138 - 100 - 16 = 22
This elevated result may indicate a high anion gap, which would lead to review of causes like lactic acid buildup, ketoacidosis, renal failure, or toxic alcohol ingestion. The ultimate reading depends on symptoms, history, and the rest of the blood chemistry.
Limits and Clinical Considerations
Even a well-designed Anion Gap Calculator has limitations. One important concern is correction for albumin. Because albumin affects the gap, a patient with low albumin may have a misleadingly low or normal result unless a albumin-corrected anion gap is considered.
Test variability is another important factor. Different analyzers and local methods can lead to slightly different sodium, chloride, and bicarbonate results. So the calculator output may shift depending on where the sample was processed. For that reason, comparison with the relevant reference range is essential.
Clinical judgment also matters. A numerical result should be read in light of symptoms, medication use, recent illness, and the larger pattern of serum electrolytes. Sometimes an arterial blood gas test is needed to better define the acid-base status, especially when the bicarbonate level and clinical presentation do not match the calculated gap.
In other words, the calculator is useful, but it is not a substitute for professional evaluation. It works best as part of a complete assessment of clinical context, especially when the result could signal a serious disorder or a rapidly changing condition.
Frequently Asked Questions
How do you calculate the anion gap using chloride and bicarbonate values?
Use the usual formula for anion gap: sodium minus chloride minus bicarbonate, often written as Na - Cl - HCO3. Enter the Na, Cl, and bicarbonate values into an Anion Gap Calculator, or calculate it manually by subtracting chloride and bicarbonate from sodium. Some formulas also include potassium, so check which version is being used.
What is a normal anion gap range?
A normal anion gap varies with the lab and the formula used, so the best reference is the local reference range. Many labs provide a range that is based on their analyzer and whether potassium is included. Always read the number using the lab’s own laboratory reference interval rather than assuming one universal value.
What does a high anion gap mean?
A high anion gap often means there are extra unmeasured anions in the blood, which can happen in metabolic acidosis. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. The result should be interpreted with the patient’s signs, bicarbonate level, and overall clinical context.
Can low albumin affect the anion gap result?
Yes. Hypoalbuminemia can lower the measured anion gap because albumin is a major unmeasured anion. In that situation, a corrected anion gap may be more informative than the raw value. If albumin is low, the calculator result may miss the true acid-base abnormality.
How accurate is an Anion Gap Calculator?
The calculator is usually precise for the numbers entered, but the final meaning depends on the quality of the lab results and the way the formula is set up. Lab error, lab variability, and missing albumin information can affect the result. So while it is a useful screening tool and diagnostic aid, it should always be paired with clinical judgment and, when needed, additional testing such as an arterial blood gas.
If you are using the calculator and the result seems unexpected, review the input values, confirm the chloride values and bicarbonate values, and consider whether a corrected value is needed before making a conclusion about the patient’s acid-base balance.