What exactly is the Anion Gap?
The anion gap is a calculated value used to help interpret serum electrolytes and detect possible problems in acid-base balance. It reflects the difference between the main measured positively charged particles and negatively charged particles in the blood. In practical terms, it assists clinicians and patients understand whether an unexpected acid is present in the body.
The calculation is based mainly on sodium, chloride, and serum bicarbonate, which are part of a standard serum electrolyte panel. These values come from common blood chemistry or serum chemistry testing. Because unmeasured ions also contribute to the total, the result is an estimation of anion concentration rather than a direct measurement.
An elevated or reduced gap can point toward an acid-base disorder, especially metabolic acidosis. That makes the anion gap a useful diagnostic aid in laboratory interpretation and clinical assessment. It is not a standalone diagnosis, but it can rapidly guide further evaluation.
How the Anion Gap Calculator Works
An anion gap calculator applies a straightforward formula based on routine laboratory values. The standard version is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some versions also include potassium in the formula:
Anion gap = Sodium + Potassium − (Chloride + Bicarbonate)
Because potassium is typically present in a smaller concentration than sodium, many clinicians choose the first version for routine use. Even so, the choice of formula depends on the method used by the laboratory and the type of result interpretation being applied.
That electrolyte formula is part of a broader approach to electrolyte analysis. It helps clinicians calculate anion gap values in the setting of suspected acid-base problems, especially when reviewing a serum electrolyte panel alongside the patient’s symptoms and other test results.
When the gap is higher than expected, it can suggest that unmeasured acids are accumulating. When it is less than expected, it may indicate changes in albumin, abnormal proteins, or a measurement issue. In both cases, the number must be interpreted in context, not in isolation.
Using the Internet Calculator
Using online tool is easy. Input the available input values from your laboratory results, including serum sodium, serum chloride, and serum bicarbonate. When the calculator includes a potassium option, you may also enter potassium when instructed.
Before getting started, make sure the numbers come from the same sample and are reported in the same unit system. Minor variations in collection timing or reporting methods can affect the outcome. A reliable medical calculator should allow quick entry while still supporting accurate electrolyte analysis.
After inputting the serum sodium and serum chloride values, the calculator performs the subtraction automatically and presents the estimated anion gap. Some tools may also offer an albumin correction option if serum albumin is available. That adjustment can enhance result interpretation when protein levels are abnormal.
For best use, think of the calculator as a efficient way to structure data from a serum electrolyte panel. It does not replace medical judgment, but it can support a focused review of the patient’s laboratory interpretation and possible electrolyte imbalance.
Typical Anion Gap Range and Meaning
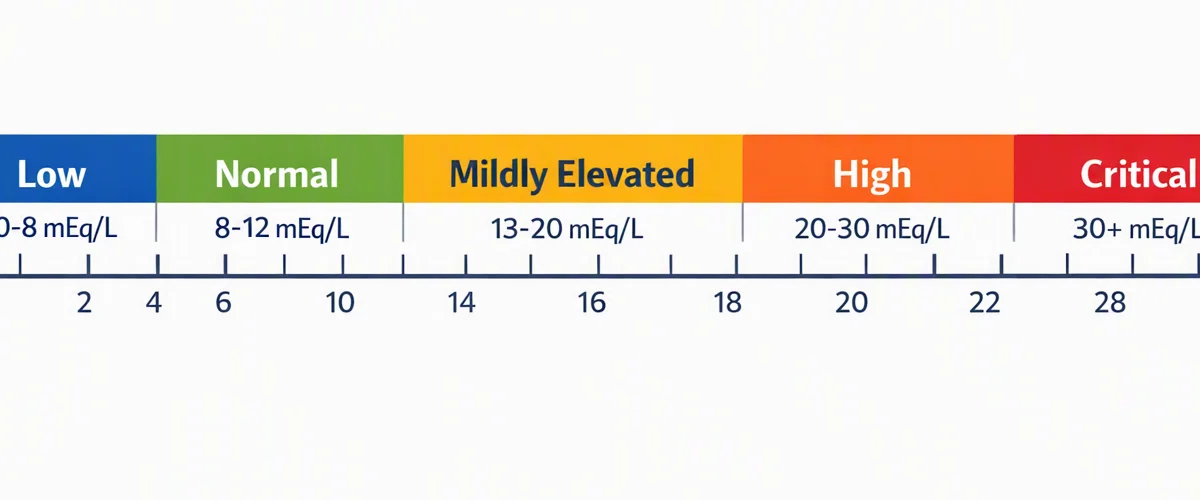
The reference range for the anion gap depends on the testing method, the formula used, and the measurement site. For that reason, each result should be compared with the lab-specific reference range. A value that is normal in one lab may be a little different in another.
In general, the anion gap is used as part of acid-base evaluation assessment. A higher-than-expected value often points to a elevated anion gap state, while a reduced value may point to a reduced anion gap. Both can be clinically meaningful, but the meaning depends on the full picture of the patient’s acid-base condition.
Clinicians often review the number alongside pH, bicarbonate, and other electrolytes to determine whether there is an acid-base disorder. A normal gap does not exclude illness, and an abnormal gap does not identify the exact cause on its own. It simply reduces the possibilities and helps with clinical evaluation.
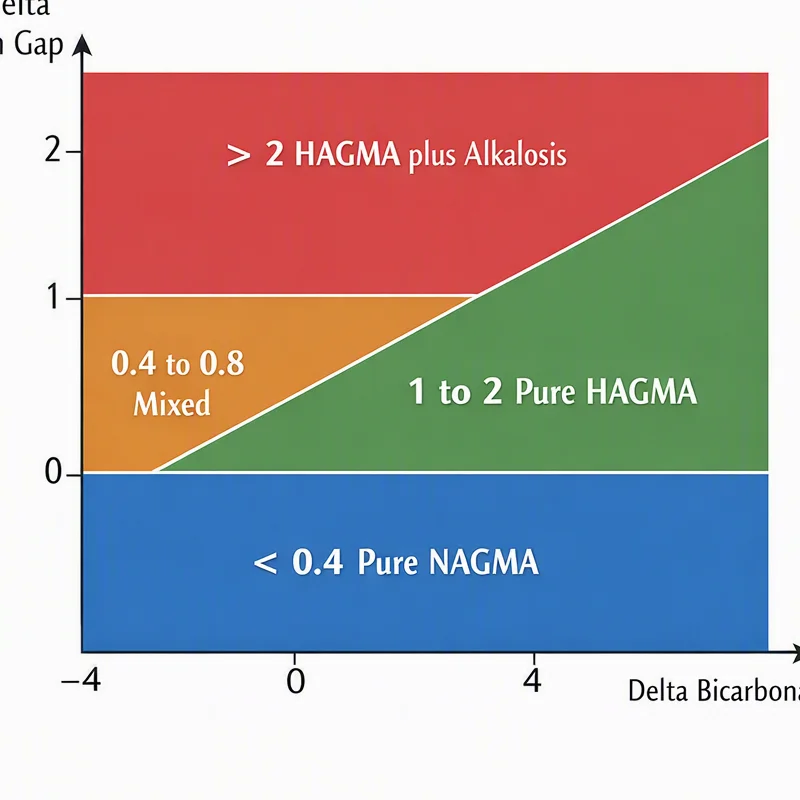
One important point is that a normal result does not always rule out all forms of acidosis. Some patients have a non-anion gap acidosis, which means bicarbonate is low but the gap is not elevated. That pattern requires a different assessment than high anion gap acidosis.
Elevated Anion Gap Causes
A increased anion gap often means there are extra acids in the blood that are not directly measured by standard electrolytes. This result is central to metabolic acidosis evaluation and should warrant review of the patient’s complaints, background, and additional labs.
Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. Each of these conditions increases unmeasured acid in the bloodstream, which raises the calculated gap.
- Lactic acidosis can occur when the body makes too much lactate or cannot clear it efficiently. Ketoacidosis is frequently associated with uncontrolled diabetes, starvation, or heavy alcohol use. Renal failure can impair the body’s ability to clear acids effectively. Toxic alcohols, such as certain ingested solvents, can produce severe metabolic disturbance.
These causes are not exhaustive, but they represent the most commonly discussed categories in laboratory interpretation. A elevated result should be treated as a signal to look deeper rather than a final diagnosis. The calculator helps identify the abnormality, but the underlying cause still requires focused evaluation.
Decreased Anion Gap Causes
A low anion gap is less common, but it can be equally important. One of the most frequent explanations is hypoalbuminemia, because albumin is a key unmeasured negatively charged protein in the blood. When albumin falls, the calculated gap may also drop.
Other possible causes are multiple myeloma, where abnormal proteins can affect the gap, and lab error, which should always be carefully be considered when a result seems surprising. Certain electrolyte changes, including hypercalcemia, may also play a role in a reduced value in some cases.
When a low result appears, the first step is often to confirm the measurement and confirm there is no lab error. Then clinicians review total protein, albumin, and the broader picture of electrolyte imbalance. A low gap is not always harmful, but it should not be ignored if the value is persistently abnormal.
Because low values can reflect changes in protein or measurement rather than acid production, they require thoughtful interpretation. The calculator can detect the pattern, but only a clinician can determine whether the finding is meaningful in the current clinical setting.
Albumin Adjustment and Patient Context
Correction for albumin is important because blood albumin has a major effect on the anion gap. When albumin is low, the calculated number may underestimate the true level of unmeasured acids. Correcting for albumin can therefore offer a more accurate corrected anion gap.
This correction is especially useful when evaluating a patient with suspected acid buildup or when looking for hidden abnormalities in nutritional status. A person with low albumin may seem to have a near-normal gap even when significant acid accumulation is present. In that case, failing to correct for albumin could result in a missed clue during clinical assessment.
Correction for albumin does not replace the original calculation. Instead, it provides context. A clinician may assess both the raw and corrected values to understand whether a low albumin level is masking a elevated anion gap. This is one reason the anion gap is best used as part of a larger diagnostic review rather than as a single-number answer.
When available, albumin should be interpreted alongside the rest of the serum chemistry panel. That broader view helps connect the calculator output to the patient’s actual physiology and improves clinical interpretation.
Limitations of the Calculator
An online calculator is a useful screening tool, but it has clear limitations. It depends on precise entry of data, consistent lab methods, and proper clinical context. Even small differences in laboratory variability can change the apparent result.
The tool cannot make a clinical diagnosis by itself. It can show whether the gap is higher than or under the expected reference range, but it cannot determine the full cause of the abnormality. That requires review of symptoms, history, medications, other tests, and the overall electrolyte imbalance.
Another limitation is that the calculator does not account for every factor that affects acid-base status. Different laboratories may use slightly different methods, and the same patient may show different numbers under different conditions. This is why any abnormal value should be checked against the broader picture of acid-base balance and not treated as a standalone answer.
Used correctly, the calculator is a useful diagnostic aid for quick review, but it is still only one part of a larger clinical assessment. It helps thinking; it does not replace it.
Frequently Asked Questions About Anion Gap Calculation
What does an anion gap calculator used for?
An anion gap calculator is used to rapidly estimate the anion gap from basic laboratory values such as serum sodium, serum chloride, and serum bicarbonate. It helps with laboratory interpretation, especially when evaluating metabolic acidosis and other acid-base disorder patterns. It is a useful medical calculator for reviewing a serum electrolyte panel and guiding further assessment.
What is a normal anion gap range?
The normal range depends on the lab’s method and the formula being used, so the best comparison is the local reference range. In general, the result should be interpreted in the context of the specific lab report. A value outside the expected range may suggest a https://anion-gap-range805.almoheet-travel.com/anion-gap-calculator-with-corrected-sodium high anion gap or low anion gap, but the meaning depends on the rest of the clinical picture.
What leads to a high anion gap?
Frequent causes of a high anion gap include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. Such conditions raise unmeasured acids in the blood and can signal a serious metabolic acidosis. A high result should always be followed by more thorough clinical assessment rather than being used as a final diagnosis.
Why is albumin correction be important in anion gap calculation?
Albumin correction matters because low serum albumin can lower the measured gap and obscure a true abnormality. Calculating a corrected anion gap helps adjust for changes in protein status and can reveal a more accurate estimate of unmeasured acids. This is most useful when reviewing suspected high gap acidosis.
Can a calculator diagnose the cause of an abnormal anion gap?
No. The calculator is a helpful screening tool and diagnostic aid, but it cannot diagnose the cause on its own. It can reveal whether there is an abnormal result, but the underlying cause still requires medical evaluation, review of electrolytes, and review of other findings. Conditions such as hypoalbuminemia, multiple myeloma, lab error, and broader electrolyte imbalance must all be interpreted in context.