What the Anion Gap Indicates
The anion gap is a practical way to look at electrolytes and identify hidden shifts in acid-base balance. It shows the difference between measured cations and measured anions in the blood, mainly using sodium, chloride, and bicarbonate. In practical terms, it helps clinicians recognize whether there are extra unmeasured anions contributing to a metabolic disturbance.
The concept is important because routine serum electrolytes do not capture every charged particle in the bloodstream. The anion gap therefore acts as a diagnostic tool for finding electrolyte abnormalities and narrowing the differential diagnosis in acid-base disorders. A normal or elevated value can suggest very different processes, so understanding the pattern matters as much as the number itself.
In many cases, the anion gap provides a fast view of how the body’s buffer system is responding to illness. When acids accumulate, the body may consume bicarbonate and alter the relationship among sodium, chloride, and other ions. That is why the anion gap is often reviewed alongside other lab results during clinical interpretation.
How to Work Out the Anion Gap
The standard anion gap formula is:
anion gap = sodium - (chloride + bicarbonate)Some clinicians also include potassium in the calculation, though many everyday calculations exclude it because potassium adds relatively little to the result. A frequent form that includes potassium is:
anion gap = sodium + potassium - (chloride + bicarbonate)The values used come from a serum chemistry panel, which usually reports sodium, chloride, bicarbonate, and sometimes potassium. Because the result depends on the quality of those measurements, the calculation is only as reliable as the collected specimen and lab methods.
Knowing the formula helps with lab interpretation. A low bicarbonate level can suggest metabolic acidosis, while higher chloride https://anion-gap-test918.evergrovio.com/posts/anion-gap-calculator-for-evaluating-acidemia may indicate a compensatory pattern or a certain acid-base process. The anion gap does not replace full diagnostic review, but it helps organize the first step of diagnostic evaluation.
How to use an Anion Gap Calculator
An Anion Gap Calculator applies the formula and reduces manual error when checking lab values. It is especially useful when multiple results need to be interpreted efficiently, such as in urgent care settings, emergency assessment, or inpatient monitoring. By entering sodium, chloride, bicarbonate, and sometimes potassium, the calculator returns the anion gap and helps identify the pattern.
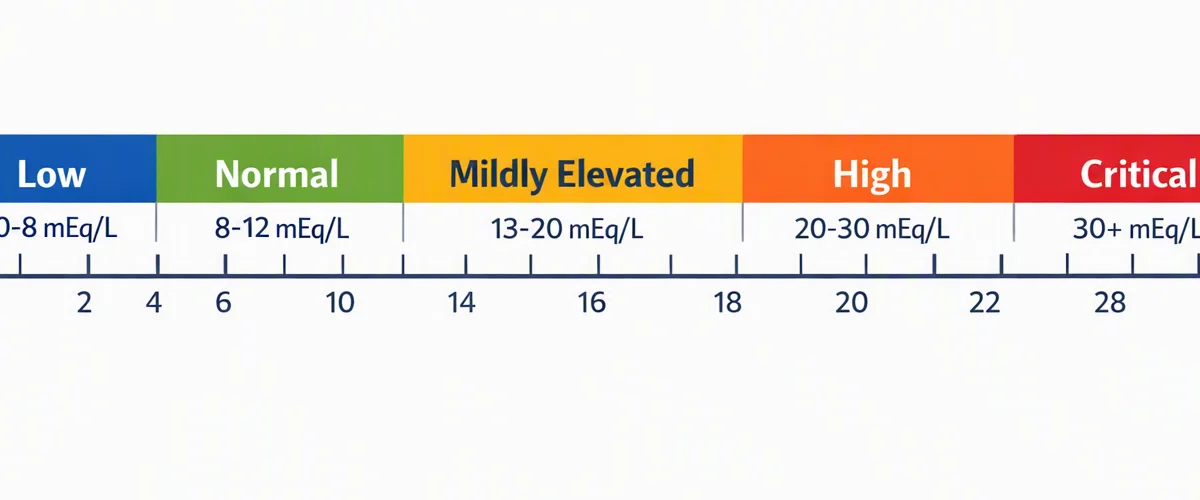
Most calculator outputs should be compared with the lab’s reference range, since the exact normal interval can vary by analyzer and institution. A value that appears near the limit in one system may be normal in another. That is why the same number should always be interpreted in context rather than in isolation.
Used correctly, the calculator supports recognition of electrolyte imbalance and helps guide the next clinical step. It can flag whether a patient may have a high-gap process, a normal-gap process, or a mixed disorder. In other words, it is a starting point for clinical interpretation, not the final answer.
Typical Anion Gap vs Increased Anion Gap
Standard anion gap metabolic acidosis and increased anion gap metabolic acidosis are two primary patterns within metabolic acidosis. Both feature a reduction in bicarbonate, but the way chloride and unmeasured acids change is not the same. Identifying the pattern is important because it narrows the origin of the acid-base disorder.
In typical anion gap metabolic acidosis, bicarbonate is decreased and chloride rises to preserve electrical neutrality. This is often called a hyperchloremic pattern. In increased anion gap metabolic acidosis, bicarbonate declines because acids build up, leaving behind excess unmeasured anions that raise the gap.
The distinction matters because it changes the differential diagnosis. A normal-anion-gap pattern often points toward GI or renal bicarbonate loss, while a increased-gap pattern suggests more acid production or reduced elimination of acids. The calculator helps clarify the direction, but the complete assessment requires symptoms, history, and other labs.
Typical Sources of Increased Anion Gap
Various common issues can cause a elevated gap. Lactic acidosis develops when lactate accumulates, often due to tissue hypoperfusion, severe illness, or impaired oxygen delivery. Ketoacidosis can occur with diabetes, starvation, or alcohol use, leading to increased ketoacids in the blood.
Renal failure is another major factor because the kidneys cannot remove acids effectively. As acid accumulates, bicarbonate is consumed and the anion gap increases. This pattern is often found alongside other laboratory changes that reflect reduced kidney function.
Toxic alcohols are an essential consideration in the right clinical setting. Ingestions such as methanol or ethylene glycol can produce acid metabolites that raise the gap and create serious toxicity. Because these cases can progress rapidly, the anion gap is one piece of a broader emergency diagnostic evaluation.
Sources of Regular Anion Gap Metabolic Acidosis
When the anion gap stays unchanged in the presence of acidosis, the problem is often related to straightforward bicarbonate loss or impaired acid excretion. Diarrhea is a usual cause because gastrointestinal fluid loss removes bicarbonate from the body. The kidneys may adjust by holding on to chloride, producing a normal-gap pattern.
Renal tubular acidosis is another important cause. In this condition, the kidneys cannot properly manage acid secretion or bicarbonate reabsorption, which leads to hyperchloremic acidosis. The chloride rise counteracts the bicarbonate loss, so the anion gap may stay within the usual range.
These causes are often overlooked if only the final number is reviewed. The clinician must consider hydration status, medication use, kidney function, and recent gastrointestinal losses. A calculator can reveal the pattern, but it cannot by itself determine the underlying source of the metabolic disturbance.
Revised Anion Gap and Serum Albumin Adjustment
Albumin is a important unmeasured negative ion in the blood, so it has a strong influence on the calculated result. When albumin is low, the measured anion gap may appear falsely normal or only slightly elevated. This is why the corrected anion gap is often used to improve lab interpretation.
Hypoalbuminemia can hide a true high-gap process. In a patient with low serum albumin, the apparent gap may underestimate the number of unmeasured anions. Using a correction formula helps adjust for that loss and gives a more accurate view of acid-base status.
Correcting for albumin is especially useful in critically ill patients, malnutrition, liver disease, or other conditions where albumin may be reduced. The adjusted result improves clinical interpretation and can expose a hidden high-gap state that would otherwise be missed. In practice, the corrected value should be viewed alongside the overall clinical picture rather than used alone.
How to Interpret Results Within the Clinical Context
The anion gap becomes especially useful when paired with the rest of the workup. A blood gas can confirm whether a patient has acidemia or alkalemia, while the electrolyte panel helps define the pattern of sodium, chloride, and bicarbonate changes. Together, these data support a more complete clinical evaluation.
When a high gap is present, it is often important to ask whether the patient also has an elevated osmolar gap. That can point toward toxic alcohol exposure in the right context. When a normal gap is present, the clinician may consider gastrointestinal bicarbonate loss, renal acidification defects, or iatrogenic causes.
Interpretation should also weigh symptoms, vital signs, medication history, kidney function, and timing of the abnormality. The anion gap is a risk assessment tool, not a diagnosis by itself. Its real value lies in guiding the next steps in evaluation and deciding how urgently to act.
Limitations and Common Pitfalls
Even a well-constructed calculator can be affected by measurement error or lab artifact. If one electrolyte is inaccurate, the derived anion gap can be misleading. That is why suspicious results should be repeated and reviewed against the broader clinical picture when necessary.
Another issue is the reference interval. Different labs use different methods, so the definition of “normal” may vary. A value that seems abnormal on one report may fall within another lab’s accepted range. This is one reason a calculator should always be paired with local lab standards.
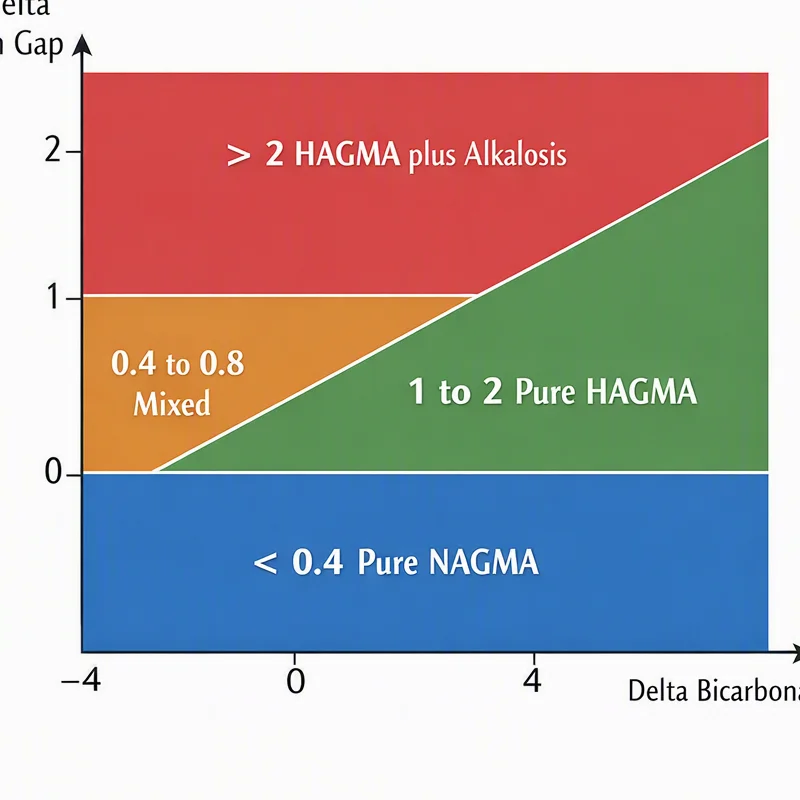
The delta gap is a valuable advanced concept when the clinician suspects a mixed disorder. It compares the change in anion gap with the change in bicarbonate and helps determine whether more than one acid-base process is happening at once. This is particularly helpful when the pattern does not fit neatly into a single category.
Common Questions
How is an Anion Gap Calculator used?
An Anion Gap Calculator is used to calculate the anion gap from serum electrolytes and help identify electrolyte abnormalities and acid-base disorders. It supports the evaluation of metabolic acidosis, helps tell apart between high-gap and normal-gap patterns, and supports clinical interpretation of lab results.
What range is considered a normal anion gap?
The anion gap normal range depends on the laboratory method and the reference range used by that lab. Because measurement techniques differ, the best approach is to compare the result with the local reference interval rather than relying on a single universal cutoff.
Why does low albumin affect the anion gap?
Low albumin decreases the amount of unmeasured anions in the blood, which can make the measured gap appear falsely low or normal. That is why albumin correction and the corrected anion gap are valuable in patients with hypoalbuminemia.
What can cause a high anion gap?
Common causes of a high gap include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. These conditions introduce acids or reduce acid clearance, increasing the concentration of unmeasured anions and producing high anion gap metabolic acidosis.
Can a normal anion gap still indicate a serious electrolyte abnormality?
Yes. A normal gap can still reflect important disease, especially normal anion gap metabolic acidosis from diarrhea or renal tubular acidosis. It may also represent an early or mixed disorder, so the full clinical evaluation and related lab data matter as much as the gap itself.